
Classification framework
Getting more from Bloom’s taxonomy
What are we asking learners to do with their knowledge, and do our teaching and assessments give them a chance to do it?
Original article: Simon Carley · 2015-11-04
Updated 21 October 2026 · 5 min read
Bloom’s taxonomy is a classification system. That’s what taxonomy means. It earns its place in this collection because it helps us think about something that matters a great deal in emergency medicine: what we expect people to do with what they know.
We spend much of a shift making decisions with incomplete information. Knowing the textbook account of a condition helps, of course, but we also have to decide which parts apply to the person in front of us and what to do about the bits that don’t quite fit. If we want our learners to get better at that, we need to give them some practice at it. A teaching programme consisting entirely of facts followed by questions about those facts will leave rather a lot out.
Which version are we using?
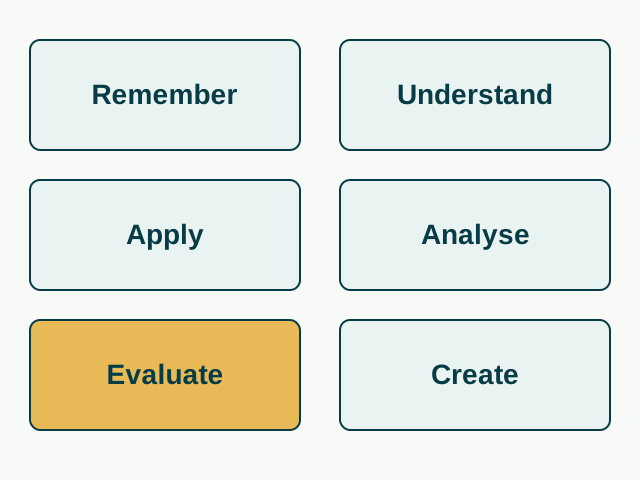
The original cognitive taxonomy appeared in 1956. Anderson, Krathwohl and colleagues revised it in 2001, and it’s that revision we’re discussing here. In Krathwohl’s explanation, the six cognitive processes are remember, understand, apply, analyse, evaluate and create. The revision also distinguishes factual, conceptual, procedural and metacognitive knowledge. So we can ask both what someone knows and what we want them to do with it.
It’s often drawn as a pyramid. Take care with that. The revised categories overlap, and they don’t prescribe six separate stages for every teaching session. Nor do they divide neatly into things medical students do at the bottom and things consultants do at the top. A consultant still needs to remember things. A medical student can begin to weigh up competing explanations with suitable help.
Think about the questions you ask
Suppose you’re discussing a patient with chest pain after the immediate clinical work is done. You could ask the learner to list possible diagnoses. There’s a place for that question, especially if you’re trying to find out what they already know. But where does the conversation go next?
Ask which details made one explanation more likely than another. Ask why a particular investigation was included in their plan. Change a feature of the case and explore whether they’d still make the same decision. You’re now finding out how they use the information, and you have a better chance of discovering where they’re struggling.
Perhaps they haven’t learnt a relevant fact. Perhaps they know it perfectly well but haven’t understood its importance in this situation. Those problems need different teaching. Going through the same slide again might help with the first; it could leave the second completely untouched.
With a more experienced group, you might ask them to compare two defensible plans and explain what would make them choose between them. They could then work out how to explain the uncertainty to a patient. The discussion will probably move back and forth between several of Bloom’s categories. That’s fine. Nobody needs to stop the conversation to announce that we’ve reached “evaluate”.
The learning objective is there to help you
“Understand chest pain” sounds reasonable until we try to work out whether the session achieved it. What would we accept as evidence? Remembering a list? Explaining a decision? Conducting the consultation?
For the discussion above, we might want the learner to explain why two patients need different investigation plans and what uncertainty remains in each case. That gives us something to prepare for. We need suitable cases and enough time for the learner to think aloud. We also need to hear their explanation, rather than spend the whole session giving ours.
This is where Bloom is useful when planning teaching: put the objective alongside the activity and whatever you’ll use to check learning. Do they fit? If the objective asks learners to weigh up alternatives, have we given them an opportunity to do that?
Be wary of solving this by choosing a grander verb from a list. “Evaluate” can still produce a rehearsed answer if everyone knows exactly which answer the teacher wants. The case and the question matter, as does what we do when the learner offers a view we weren’t expecting.
A word about MCQs
There’s a correction to make to the earlier version of this article, which suggested that MCQs were unlikely to be appropriate for senior trainees and consultants. That was too sweeping. The NBME item-writing guide explains how clinical vignettes can ask candidates to interpret information and apply their knowledge. An MCQ needn’t be a test of an isolated fact.
Equally, choosing an answer doesn’t show us how somebody will conduct a difficult conversation. That’s where Miller’s pyramid helps. We also need to remember the skills and attitudes involved in clinical work. The cognitive taxonomy covers a great deal, but it won’t tell us whether a clinician listens when a patient disagrees.
Learning point: Have a look at a session you already teach. What do the learners actually get to do? If you want them to become better at clinical decisions, make sure some of the time is spent letting them make and explain those decisions. Bloom gives us a way to check whether we’ve allowed for that.
References and further reading
- Krathwohl DR. A revision of Bloom’s taxonomy: an overview. 2002.
- NBME. Item-Writing Guide, sixth edition: testing application of knowledge.